

Treatment-resistant depression (TRD) usually means your depression has not lifted after you tried two or more antidepressants, each at an adequate dose for long enough. It is common, it is not a personal failing, and it does not mean you are out of options. In our work, the people who come to us with TRD are often tired more than anything. They have done what they were asked to do, and they still feel flat. There are other steps, and we walk through them below.
TL;DR
- TRD most often means persistent symptoms after two or more antidepressants, each tried for several months, according to NAMI.
- Before calling depression “resistant,” a careful clinician rechecks the diagnosis, the doses, the timing, adherence, and other conditions that can mimic or worsen depression.
- Options include adjusting or augmenting medication, therapy, TMS, Spravato (esketamine), and ketamine infusions. Which one fits depends on your history and goals.
- If you are having thoughts of suicide, call or text 988 right away. Do not wait for an appointment.
Table of Contents
- What treatment-resistant depression means
- Before we call it resistant: what we reassess
- Medication options when the first antidepressants fall short
- Interventional options: TMS, Spravato, and ketamine
- Who ketamine-based treatment may suit, and how to use it safely
- Our perspective
- How to start
- When to get help right away
- FAQ
- Sources
What treatment-resistant depression means
There is no single definition everyone agrees on. The most common one is the one above: two or more antidepressants, each tried for several months, with symptoms still present. A 2024 American Family Physician review frames it as failing to reach remission after at least two antidepressant trials, and reports that TRD occurs in up to 31% of people with major depressive disorder.
That is a lot of people. If you are one of them, you are in large company, even if it feels isolated from the inside.
What does it feel like? Often it looks like ordinary depression that has simply refused to move. Low mood, loss of interest, poor sleep, trouble concentrating, a heavy sense of effort in small tasks. Sometimes the first medication took the edge off and then stopped helping. Sometimes nothing helped at all. Partial response is also real, and it matters: feeling 30 percent better is not the same as feeling well, and we do not treat it as “good enough.”
A word on the label itself. Health Canada’s advisory committee has pointed out that the two-failed-trials rule is useful but limited, and that no definition has proven strongly predictive (consensus statements). We agree with that spirit. The number matters less than the question behind it: what has actually been tried, and what should we try next?
Before we call it resistant: what we reassess
This step surprises people. Before settling on TRD, we go back over the story. In our experience, a fair number of “failed” treatments turn out not to have been quite what they seemed.
The AFP review says clinicians should verify the diagnosis, the dose and duration of each medication, and adherence, and should look for other medical or psychiatric conditions that complicate depression. A 2026 consensus panel in the Journal of Clinical Psychiatry describes resistance as a continuum and lists things that can look like nonresponse, including:
- misdiagnosis or bipolar-spectrum illness
- trauma-related disorders
- substance use
- sleep apnea
- thyroid disease
- chronic pain
- missed doses
- side effects that were hard to tolerate
Bipolar disorder deserves its own mention. The AFP review recommends screening for mania or hypomania when depression treatment has not worked, because standard antidepressants alone may not be the right tool in that case. We ask about past stretches of unusually high energy, little need for sleep, or racing thoughts. Many people have never been asked.
Building a treatment timeline
A published assessment guide in the Journal of Clinical Psychiatry recommends reviewing each prior treatment: the medication or therapy, dose, timing, length, adherence, side effects, response, and why it ended. Records, pharmacy data, and input from family can help fill gaps.
You can help by writing down what you remember before your visit. Rough is fine. Names of medications, about when you took them, whether anything helped even a little, and why you stopped. If you want a sense of how clinicians use symptom scores to judge progress over time, this overview of PHQ-9 follow-up timelines is a helpful companion.
The same guide says the goal of assessment is to clarify the illness, learn what you want from treatment, and choose what is most likely to work for you now, not follow a fixed sequence. We think about it the same way.
Medication options when the first antidepressants fall short
Medication changes are usually the first stop, and they are often worth a real try. According to NAMI, a clinician may raise a dose that was too low, switch to a different antidepressant, add a second antidepressant, or add a medication that is normally used for another psychiatric condition. The AFP review lists switching class, adding psychotherapy, or augmenting with options such as a second-generation antidepressant, an atypical antipsychotic, a tricyclic, lithium, or triiodothyronine.
NAMI also names two FDA-approved medications for TRD: olanzapine/fluoxetine (Symbyax) and intranasal esketamine (Spravato).
Augmentation is a topic we have written about for clinicians, including how large the benefit tends to be. If you want the more technical version, see our augmentation strategies for depression page.
Psychotherapy deserves a quiet mention too. It is not a consolation prize. Combined with medication changes, it is one of the core strategies the AFP review lists for partial response or TRD.
Interventional options: TMS, Spravato, and ketamine
When several medication steps have not been enough, we usually talk about interventional treatments. These work differently from a daily pill, and for some people that difference is the point. The AFP review notes that rTMS, electroconvulsive therapy, ketamine, and esketamine may all be considered for TRD.
Here is how the ones we offer compare at a glance.
| Option | What it is | How it is given | Where to read more |
|---|---|---|---|
| TMS | Magnetic pulses directed at a mood-related brain area | Outpatient sessions, no anesthesia | TMS therapy |
| Spravato (esketamine) | FDA-approved nasal spray for TRD | In a medical setting with monitoring | Spravato therapy |
| Ketamine infusion | Low-dose intravenous ketamine | In a clinic under medical supervision | Ketamine therapy |
Transcranial magnetic stimulation
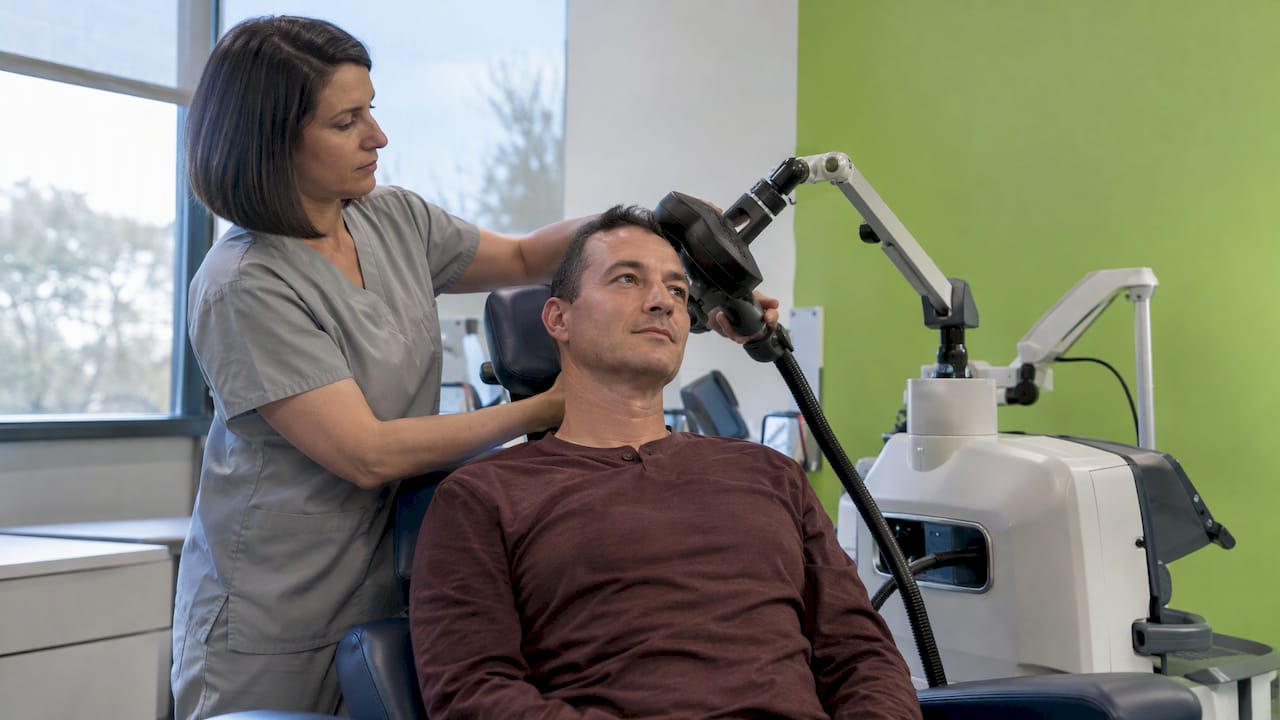
TMS is a non-medication option. You sit comfortably, awake, while a coil delivers magnetic pulses to a targeted area of the brain. There is no sedation, so many people return to normal activities afterward. If you are curious about the mechanics, we explain them in how TMS therapy works, and we compare it directly with pills in TMS therapy vs. medication.
Spravato (esketamine)
Spravato is the FDA-approved form. NIH describes esketamine as a nasal spray given in a doctor’s office, clinic, or hospital. Harvard Health reports that in studies it improved depression scores in the short term more than placebo, and that in a longer study, nasal esketamine plus a regular antidepressant helped people stay in remission through 16 weeks (Harvard Health). If you are wondering about logistics, our guide for beginners covers what a visit looks like, and we have a step-by-step page on insurance coverage for Spravato.

Ketamine infusions
This is the question we hear most. Does ketamine help depression? NIH says low intravenous doses of ketamine are used off-label for severe TRD and may improve symptoms within hours. Ketamine itself is not FDA-approved for depression, which is the difference from esketamine. NAMI likewise notes improvement can come within hours in a clinic, and that long-term effectiveness has not been established in the evidence it cites. That is why we think of ketamine as part of a plan with follow-up, not a one-off fix.
If you want more depth, these pages walk through the details:
- the difference between ketamine and esketamine
- infusions versus the nasal spray
- how ketamine works for depression
- how ketamine compares to TMS
Who ketamine-based treatment may suit, and how to use it safely
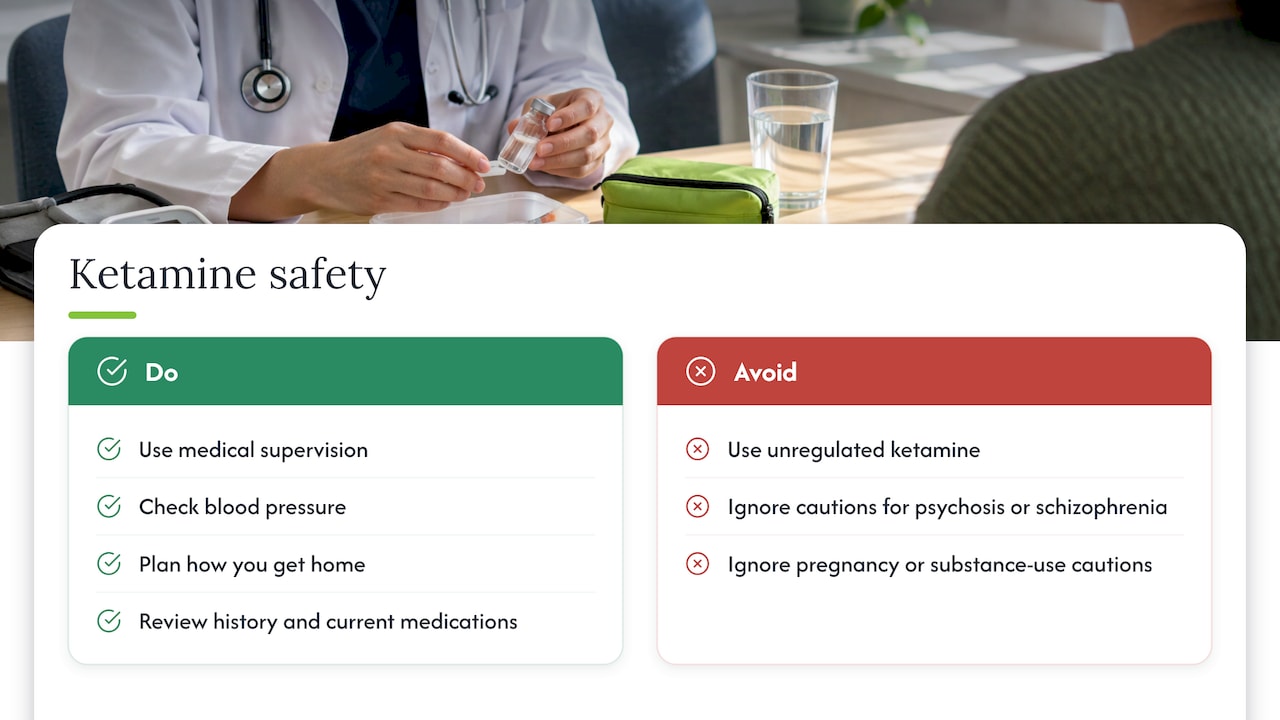
Ketamine treatment is meant to happen in a supervised setting. NIH notes that unregulated ketamine use has prompted FDA warnings, and it separates that from medically administered esketamine. That line matters to us. Medical oversight, blood pressure checks, and a plan for how you get home are part of the treatment, not extras.
Harvard Health lists the side effects and risks that we prepare patients for: dissociation, a feeling of intoxication, sedation, higher blood pressure, dizziness, headache, blurred vision, anxiety, nausea, and vomiting. It also advises avoiding ketamine, or using extreme caution, with psychosis or schizophrenia, substance-use disorder, pregnancy or breastfeeding, adolescents, and older adults with dementia symptoms, and it mentions the possibility of addiction and ketamine use disorder.
This is why a full evaluation comes first. We review your medical history, your current medications, and any history of substance use or psychosis before recommending a course. For a broader look at who tends to be a good fit, this piece on candidates for ketamine therapy offers a starting point, and we will always tailor that to you in person.
Parents sometimes ask about teens. Because of the caution above, that is a conversation to have directly with a psychiatrist rather than something to decide from an article.
Our perspective
We have learned that treatment-resistant depression is rarely one problem. More often it is a handful of small ones: a dose that was never quite right, a diagnosis that missed something, sleep that never recovered, a medication that caused side effects nobody asked about. We often notice that people arrive believing they are “the one who doesn’t respond.” We do not think that is the right way to hold it.
In our work, the first visit is mostly listening and sorting. What has been tried, what helped a bit, what hurt. From there, interventional treatments make sense for many people. TMS gives a medication-free path. Spravato gives an FDA-approved option with a medical team in the room. Ketamine infusions can act quickly, and for someone who has been struggling for months, speed can matter. We also offer stellate ganglion block for PTSD and anxiety when that is part of the picture.
None of this is a straight line. Recovery tends to be a journey, with better weeks and harder ones, and we plan for both. Our aim is to find what is most likely to work for you, to keep adjusting, and to stay with you while we do.
Felix
How to start
If you live in Allen, Frisco, McKinney, Plano, or elsewhere in North Dallas, we can see you in person or by telehealth. A first visit is about understanding your history and choosing a next step together. Bring your medication list, or a rough timeline if you do not have one.
You can read about our approach on the Nortex Psychiatry home page, or go straight to the treatment you are curious about: TMS, Spravato, ketamine, or stellate ganglion block. Our site does not publish prices, so ask our team about costs and insurance when you reach out.
When to get help right away
Depression that does not improve can become dangerous, and it is better to speak up early. If you are thinking about suicide or about harming yourself, call or text 988, the Suicide & Crisis Lifeline, which is available at any hour. If you are in immediate danger, call 911 or go to the nearest emergency room.
Also reach out to your prescriber promptly if your mood suddenly worsens, you stop eating or sleeping, or you notice a sudden surge of energy after starting a medication. Those changes are worth a same-week conversation, not a wait-and-see.
FAQ
Can treatment-resistant depression be cured?
Many people reach remission or a large improvement once the right treatment is found, though depression can return and often needs ongoing care. We prefer to talk about remission and staying well rather than a cure. Plans usually combine more than one approach, and we adjust them over time.
How do you treat depression when antidepressants don’t work?
We first recheck the diagnosis, doses, timing, and other conditions. Then options include changing or adding medications, psychotherapy, TMS, Spravato, or ketamine. The right order depends on your history, your side effects, and what you want from treatment.
Does ketamine help depression?
Low-dose IV ketamine is used off-label for severe TRD and may improve symptoms within hours, according to NIH. Long-term effectiveness has not been firmly established in the evidence NAMI cites, so we pair it with follow-up and a broader plan. It should only be given in a supervised medical setting.
What is the difference between ketamine and Spravato?
Spravato is esketamine, an FDA-approved nasal spray given in a medical setting. Ketamine is given intravenously and is used off-label for depression. Our page on ketamine and esketamine goes through the differences.
Sources
- Depression: Managing Resistance and Partial Response (American Family Physician, 2024)
- Treatment-Resistant Depression (NAMI)
- Depression (NIH Health)
- Ketamine for treatment-resistant depression (Harvard Health)
- Treatment-Resistant Depression as a Dynamic Continuum (Journal of Clinical Psychiatry)
- Developing a Treatment-Resistant Depression Consultation Program, Part 2 (Journal of Clinical Psychiatry)
- Consensus statements (Health Canada)
- 988 Suicide & Crisis Lifeline (SAMHSA)



